
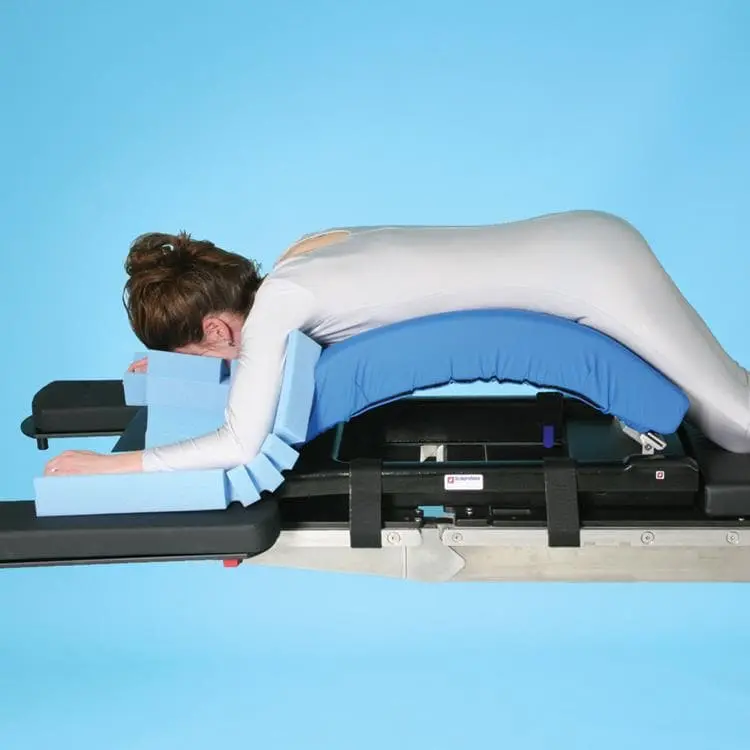
The jackknife prone position for surgery, also called the Kraske position, places the patient face down with the operating table flexed at the hips so the pelvis becomes the highest point and the head and legs angle downward. Surgeons use it mainly for anorectal, perineal, and select lumbar spine procedures. Safe use depends on keeping the abdomen free and protecting every pressure point.
This guide covers how the jackknife position differs from standard prone and lithotomy, which procedures rely on it, how it affects cardiovascular physiology, and the equipment and setup steps OR teams use to manage its risks.
What Is the Jackknife Prone Position for Surgery?
The jackknife position is a variation of the prone position. The patient lies on the abdomen with the hips flexed and both the head and legs lower than the hips (Osmosis). In practice, the team aligns the patient’s hips over the operating table’s center break, then flexes the table gradually to create the inverted “V.”
Raising the pelvis this way spreads the buttocks and brings the anal canal, perineum, and sacral region up into the surgeon’s field. It is the same geometric logic that makes the position useful for a pilonidal excision or the perineal phase of a rectal resection.
Jackknife vs. Standard Prone vs. Lithotomy
Jackknife prone differs from standard prone mainly in table flexion and pelvic elevation. For anorectal work, the main alternative is lithotomy, which places the patient on their back with legs elevated in stirrups.
| Factor | Standard prone | Prone jackknife (Kraske) | Lithotomy |
|---|---|---|---|
| Patient orientation | Face down, table flat | Face down, table flexed at hips; head and legs lowered | Supine, hips and knees flexed, legs elevated |
| Typical uses | Spine, posterior extremity, posterior trunk procedures | Anorectal procedures, perineal phase of rectal resection, select lumbar procedures | Gynecologic, urologic, and many anorectal procedures |
| Key support equipment | Chest and pelvic supports or spine frame, head support, armboards | Flexing table, chest and pelvic supports, head support, armboards, knee and foot padding | Stirrups, table rail clamps, padding at calves and heels |
| Airway access | Limited | Limited | Direct |
| Main positioning concerns | Abdominal and chest compression, ocular pressure, brachial plexus | Same as prone, plus hemodynamic shifts from flexion and head-down tilt | Peroneal and femoral nerve stretch or compression, hip strain |
When lithotomy is the better fit for a case, purpose-built lithotomy stirrups handle leg support and adjustment.
What Surgeries Use the Jackknife Position?
The jackknife position is used most often for procedures that need direct posterior access to the perineum, anus, rectum, or lower spine:
- Anorectal procedures: hemorrhoidectomy, fistulotomy, and pilonidal cyst excision. A study of elective ambulatory anorectal surgery under general anesthesia found prone jackknife to be a noninferior alternative to supine or lithotomy positioning (World Journal of Colorectal Surgery).
- Abdominoperineal resection (APR): some colorectal surgeons perform the perineal portion in prone jackknife rather than lithotomy. One comparative study in low rectal cancer reported better operative outcomes with the prone jackknife approach (comparative APR study, PMC).
- Single-level lumbar disc surgery: a randomized study of 40 patients found the jackknife position produced lower intra-abdominal pressure and less surgical-site bleeding than standard prone, and the authors favored it for healthy, nonobese patients (Journal of Neurosurgical Anesthesiology, 2011).
- Percutaneous nephrolithotomy: combining prone with jackknife flexion can raise the 12th rib and enlarge the working space for renal access, though it carries hemodynamic trade-offs covered below (Therapeutics and Clinical Risk Management, 2023).
How Does the Jackknife Position Affect Hemodynamics?
Turning any patient prone changes cardiovascular physiology. The Anesthesia Patient Safety Foundation (APSF) notes research showing an average 24% drop in cardiac index in the prone position, largely from reduced stroke volume, along with increased intrathoracic pressure and reduced inferior vena cava filling (APSF, 2024).
Jackknife flexion adds its own shifts. In a 1991 study of colorectal surgery patients, cardiac index fell when patients were turned from supine to prone, and heart rate slowed while mean arterial pressure rose once they were in jackknife; the authors judged those changes not to be a serious problem in that group (American Journal of Surgery, 1991).
Not every patient tolerates it as well. A 2023 retrospective matched analysis of percutaneous nephroscopy found a significantly higher incidence of intraoperative hypotension in the prone jackknife group than in the lateral group (Therapeutics and Clinical Risk Management, 2023). APSF also advises extreme care for patients with right ventricular dysfunction, pulmonary hypertension, or preload dependence, who may not tolerate prolonged prone positioning.
What Are the Main Risks of the Jackknife Position?
The main risks are pressure injury, peripheral nerve injury, eye injury, and abdominal or chest compression. Because jackknife is a prone variant, it carries all of the prone position’s risks plus the added load of flexion.
| Area | Risk | Protection |
|---|---|---|
| Eyes, nose, forehead, cheeks | Pressure injury; ocular ischemia from direct pressure | Prone head support with no pressure on the eyes; periodic checks |
| Chest and breasts | Pressure injury; reduced right ventricular function from chest compression | Chest supports sized to the patient; breasts free of bolster edges |
| Abdomen | Reduced venous return and visceral perfusion from compression, especially with obesity | Chest and pelvic supports that leave the abdomen free |
| Pelvis (iliac spines) and genitalia | Pressure injury | Padded pelvic support; genitalia free of compression |
| Arms and shoulders | Brachial plexus stretch, ulnar nerve compression, shoulder dislocation during turning | Padded armboards; arms slightly anterior to shoulders; axilla free of tension; elbows padded |
| Thighs | Lateral femoral cutaneous nerve injury | Padding where the thighs meet the table break |
| Knees and feet | Pressure injury | Knee padding; foot support that keeps toes off the table |
Source: Anesthesia Patient Safety Foundation, 2024
Arm placement deserves special attention because brachial plexus and ulnar injuries can develop silently over a long case. Our guide to arm abduction limits and armboard setup covers the details.
What Equipment Does the Jackknife Position Require?
Every piece of jackknife positioning equipment maps to a specific risk in the table above:
- Operating table with a center break and reliable lock: creates and holds the flexion without drift once the team sets the angle.
- Chest and pelvic supports: carry the torso so the abdomen hangs free.
- Prone head support: keeps the head neutral and the eyes free of pressure while maintaining airway access.
- Padded surgical armboards: support arms slightly anterior to the shoulders with the elbows padded.
- Knee and foot padding: protects bony contact points at the lower end of the “V.”
- Safety straps: secure the patient once the final position is set.
For posterior lumbar procedures such as laminectomies, decompressions, and disc surgery, many teams position the patient prone on a dedicated spine frame instead of flexing the table. The Schure Spine Frame adjusts intraoperatively to the desired lordosis, is C-arm compatible, and carries a patient weight capacity of 500 lbs. (227 kg). For more on matching frames and supports to spine procedures, see how to choose a surgical positioning device for spine surgery.
How Do OR Teams Set Up and Monitor the Jackknife Position?
A consistent sequence reduces both setup time and risk:
- Assess tolerance before the day of surgery. Review cardiac and pulmonary history, body habitus, and projected case length.
- Place lines before turning if needed. APSF recommends placing arterial and venous access before the position change if the arms will be tucked.
- Turn with a full team. APSF suggests five to six team members, including the surgeon, with cervical inline stabilization and a secured airway.
- Align and flex. Center the hips over the table break, then flex the table slowly while watching that the patient stays aligned.
- Check every pressure point. Confirm the abdomen is free, the eyes are clear, and all supports and pads are in place.
- Monitor immediately. Check vital signs right after positioning, and keep the bed or gurney in the room until the patient tolerates the position hemodynamically, so the team can return the patient supine quickly if needed.
- Recheck during and after the case. Reassess pressure points periodically, and evaluate for facial, lingual, and glottic edema before extubation.
Frequently Asked Questions
What is the jackknife position used for?
The jackknife position is used for procedures that need posterior access to the anus, rectum, perineum, or lower spine. Common examples include hemorrhoidectomy, fistulotomy, pilonidal cyst excision, the perineal phase of abdominoperineal resection, and some single-level lumbar disc procedures. The flexed table raises the pelvis to bring these areas into the surgical field.
Is the jackknife position the same as the Kraske position?
Yes. The prone jackknife position is also called the Kraske position. In both names, the patient lies prone with the table flexed at the hips, raising the pelvis while the head and legs angle downward. Some surgeons add knee flexion as a variation to improve exposure of the rectum and lower back.
How does jackknife differ from standard prone?
Standard prone keeps the table flat with the patient face down. Jackknife adds flexion at the hips, which elevates the pelvis and lowers the head and feet. That geometry improves perineal and anorectal exposure but adds hemodynamic shifts, such as changes in heart rate and blood pressure, on top of the cardiovascular effects of prone positioning itself.
What are the main risks of the prone jackknife position?
The main risks are pressure injuries to the face, chest, pelvis, knees, and feet; nerve injuries to the brachial plexus, ulnar nerve, and lateral femoral cutaneous nerve; eye injury from direct pressure; and reduced venous return from abdominal compression. Intraoperative hypotension is also a concern, particularly in patients with limited cardiac reserve.
What equipment is needed for jackknife positioning?
Core equipment includes an operating table with a reliable center break, chest and pelvic supports that keep the abdomen free, a prone head support that protects the eyes, padded armboards, knee and foot padding, and safety straps. Each item addresses a specific documented risk of the position rather than serving as an optional accessory.
Equip Your OR for Prone and Jackknife Cases
The jackknife position delivers exposure that few other configurations match for anorectal and select spine procedures, but only when the equipment and setup protocol account for its pressure, nerve, and hemodynamic risks. SchureMed designs and manufactures positioning equipment in Abington, Massachusetts, for exactly these demands. Request a quote or call 1-888-724-8763 to discuss the positioning setup for your prone and jackknife caseload.
